What Is PCOS / PMOS? Symptoms, How It Affects Your Period and How to Manage It
If your period has always seemed to operate according to its own mysterious schedule, there could be a reason.
Maybe your cycles are months apart, or maybe they're regular but are incredibly heavy when they do show up. You might also be dealing with acne that refuses to leave, increased facial or body hair, thinning hair, difficulty conceiving or changes in your metabolism.
For millions of people, these can be signs of Polyendocrine Metabolic Ovarian Syndrome (PMOS) - the condition you probably know by its previous name, Polycystic Ovary Syndrome (PCOS).
While the name has only recently changed, and the official roll out will happen over three years so you will likely see both PCOS and PMOS being referred for a while so it's important to know that they're referring to the same thing.
Here's what the change means, why it matters and what we currently know about PMOS.
First things first: why has PCOS been renamed PMOS?
For decades, the name Polycystic Ovary Syndrome has caused confusion, mainly due to the word 'polycystic'.
In May 2026, an international group of researchers, healthcare professionals and people living with the condition announced that PCOS would officially become Polyendocrine Metabolic Ovarian Syndrome, or PMOS. The change isn't because scientists have discovered a completely different condition. It is the same condition, but experts believe the new name describes what is actually happening in the body much more accurately. (Endocrine)
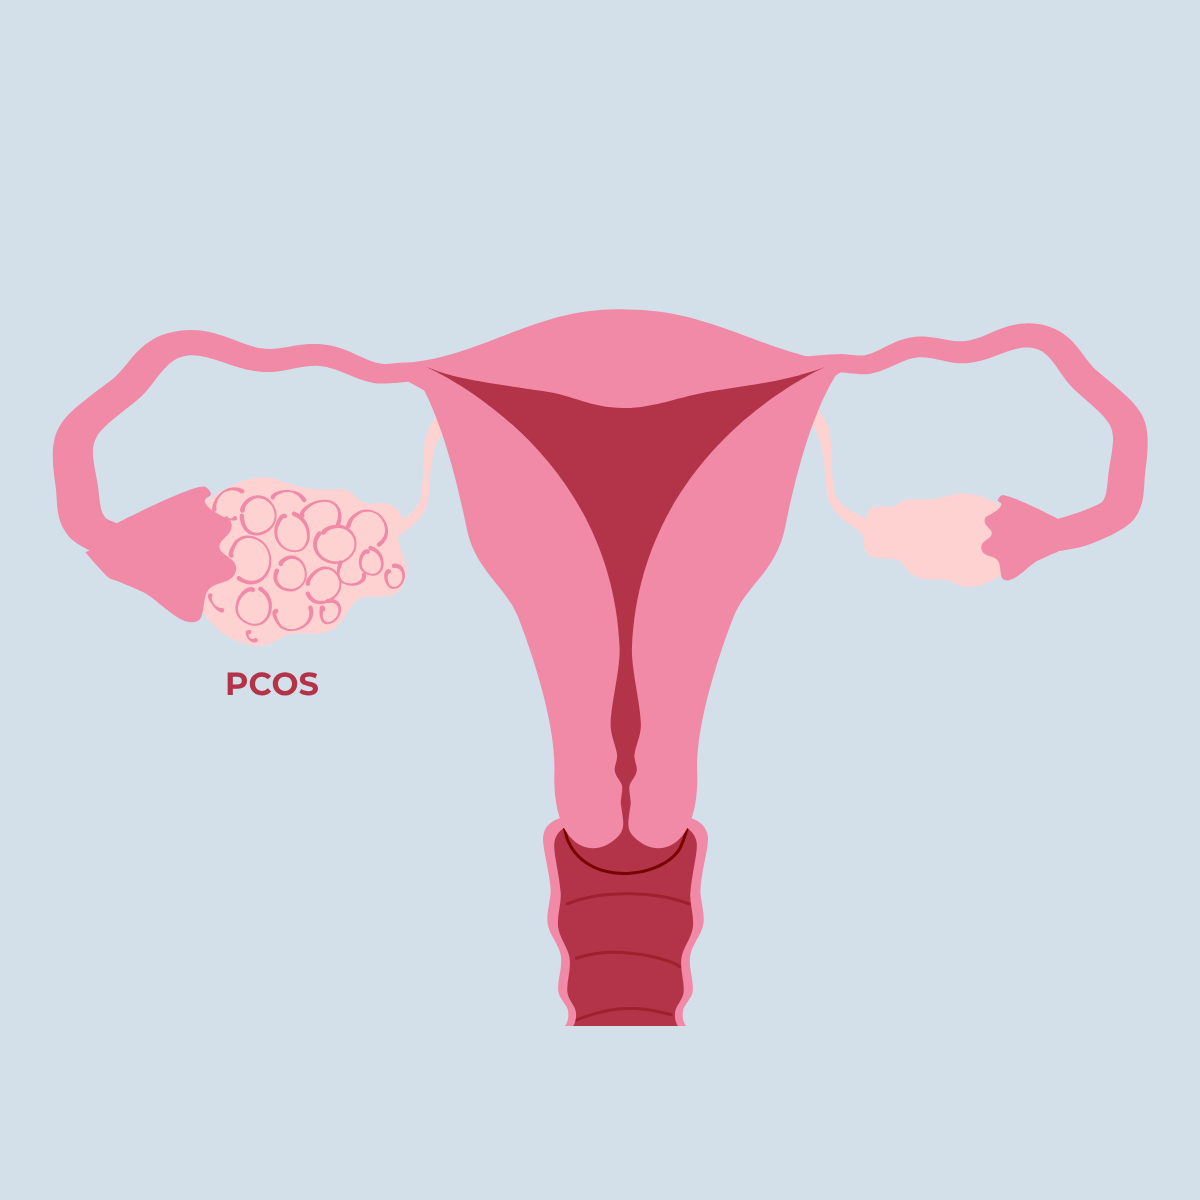
Despite what the old name suggests, you don't have to have ovarian cysts to have PCOS. In fact, the structures traditionally described as "cysts" in PCOS aren't actually abnormal ovarian cysts in the conventional sense. They are follicles associated with disrupted ovarian function.
That meant a name centred around "cysts" could give people the impression that this was primarily an ovarian condition. We now understand it is much broader than that.
PMOS can involve multiple hormone systems, metabolism, ovulation, skin and hair changes, mental wellbeing and longer-term metabolic health. Researchers behind the change say the previous name could contribute to misunderstanding, delayed diagnosis, fragmented care and an excessive focus on the ovaries rather than the whole condition. (DOI)
That's where the new name comes from:
Polyendocrine recognises that multiple hormonal systems can be involved. Metabolic acknowledges the important relationship between the condition, insulin resistance and metabolic health. Ovarian keeps the connection with ovulation and ovarian function. And, perhaps most importantly for many who have pushed for the change, the misleading reference to cysts has gone.
The name-change process was developed through years of international consultation involving people living with PCOS/PMOS, clinicians, researchers and patient organisations. The global consensus project involved 56 leading academic, clinical and patient organisations and thousands of survey responses from people with lived experience and health professionals. (DOI)
When does the PMOS name officially take effect?
While the new name Polyendocrine Metabolic Ovarian Syndrome (PMOS) was formally announced on 12 May 2026, that doesn't mean every doctor, website, medical record and health organisation suddenly switched terminology the following morning.
A three-year transition period is underway to give healthcare systems, governments, researchers, educators, medical coding systems and patient organisations time to make the change. Full implementation is planned to coincide with the 2028 International Evidence-based Guideline update. (Endocrine)
For now, you'll see wording such as "PMOS, previously known as PCOS" or "PCOS/PMOS" used frequently.
You'll notice we've done that in this article too. Millions of people know the condition as PCOS, and most existing medical information has been published using that name, so keeping both terms visible during the transition makes it easier for people to find the information they're looking for.
So, what actually is PMOS?
PMOS is a common hormonal and metabolic condition.
Current estimates suggest it affects approximately 10–13% of women of reproductive age globally, or roughly one in eight, although the exact prevalence varies depending on the population studied and diagnostic criteria used. The World Health Organization estimates that up to 70% of affected women worldwide may be undiagnosed. (World Health Organization)
PMOS is associated with changes in hormone signalling, including higher androgen activity in many people. Androgens include hormones such as testosterone.
These hormonal changes can interfere with normal follicle development and ovulation, which is why irregular periods are such a common feature of PMOS.
But here's the slightly frustrating bit: there isn't one single PMOS experience.
Someone might have irregular periods, acne and increased facial hair. Someone else might primarily experience fertility difficulties. Another person may have fairly subtle symptoms and only discover they have PMOS after investigation for something else.
It can also change throughout different stages of life.
How is PCOS / PMOS diagnosed?
There's currently no single blood test or scan that can simply tell you yes or no.
Diagnosis is based on a combination of symptoms, medical history, hormone testing and, in some circumstances, ultrasound or other assessment.
Under internationally recognised diagnostic criteria, adults are generally diagnosed when at least two of three key features are present after other possible causes have been excluded: irregular or absent ovulation, clinical or biochemical evidence of higher androgen levels, and polycystic ovarian morphology identified through appropriate assessment. (World Health Organization)
Importantly, you do not need polycystic-looking ovaries to have PMOS - one of the reasons the new name matters so much.
Diagnosis in teenagers also needs particular care. Irregular periods can be completely normal during the first stages after periods begin, and international guidelines use age-specific definitions rather than treating every irregular teenage cycle as PMOS. (PubMed Central (PMC))
If you're concerned about your cycle, it can be useful to keep track of period dates and symptoms before speaking with your GP. That gives them a clearer picture of what has been happening over time.
What are the symptoms of PMOS?
The symptoms vary enormously, which is one reason diagnosis can take time.
Irregular periods are among the most recognisable signs. Your periods might come very infrequently, disappear for months or vary significantly in length from cycle to cycle. Some people experience heavier or longer bleeding when their period finally does arrive. Others experience painful periods.
Higher androgen activity can also contribute to acne, oily skin, increased facial or body hair and thinning hair on the scalp.
PMOS is also one of the most common causes of problems with ovulation, which means some people first discover they have it when trying to conceive.
Metabolic changes can occur too. Insulin resistance is common among people with PMOS, although it is important to stress that PMOS can affect people in bodies of all sizes. You do not need to be overweight to have it, and weight alone should never be used to determine whether someone does or doesn't have PMOS. (World Health Organization)
International guidelines recognise increased rates of anxiety, depression, eating disorders and body-image difficulties among people with the condition. These aren't insignificant side effects that should simply be accepted as part of having PMOS and so it's important to pay attention to mental health too. (World Health Organization)
How does PMOS affect your period?
For many people, periods are one of the first clues something is going on.
Normally, changes in reproductive hormones encourage a follicle to develop and an egg to be released during ovulation but with PMOS, this process can be disrupted.
If ovulation isn't happening regularly, your period may not arrive on a predictable monthly schedule. You might notice longer gaps between periods or fewer periods over the course of a year. When bleeding does occur, it may sometimes be heavier or last longer.
Going for long stretches without a period is something worth discussing with your healthcare provider rather than simply putting up with. Infrequent shedding of the endometrium (your uterus lining) can increase the risk of endometrial hyperplasia and, over the longer term, endometrial cancer. The absolute risk of endometrial cancer remains low, but appropriate cycle management is still important. (World Health Organization)
Why does PMOS happen?
We still don't have one simple answer but PMOS appears to develop through an interaction between genetic, hormonal, metabolic and environmental factors.
Genetics clearly play a role. Having family members with PMOS or type 2 diabetes can increase your likelihood of developing the condition. (World Health Organization)
Insulin resistance is another important part of the picture for many people. Insulin helps move glucose from the bloodstream into cells so it can be used for energy. When the body becomes less responsive to insulin, it compensates by producing more of it. Higher insulin levels can interact with ovarian and hormonal signalling and contribute to higher androgen levels.
PMOS is complex and isn't caused by eating the "wrong" food, not exercising enough or failing to look after yourself as someone might suggest on social media.
What are the longer-term health considerations?
PMOS isn't only about periods or fertility. Because it can affect metabolic health as well as reproductive hormones, people with the condition have higher rates of insulin resistance and type 2 diabetes and should have metabolic risk factors assessed appropriately.
PMOS is also associated with increased risks of high blood pressure, abnormal cholesterol levels, sleep apnoea and complications during pregnancy. People experiencing very infrequent periods may also have an increased risk of endometrial hyperplasia and endometrial cancer. (World Health Organization)
None of this means that developing these conditions is inevitable, it does mean that PMOS deserves to be viewed as a long-term health condition rather than something that only needs attention when you're trying to become pregnant.
How can PMOS be managed?
There isn't currently a cure for PMOS, but there are plenty of ways symptoms and longer-term health risks can be managed. The right approach depends on what symptoms you're experiencing and what matters most to you.
For someone bothered by irregular periods and acne, treatment might look quite different from someone trying to conceive or someone primarily concerned about metabolic health.
Hormonal contraception is commonly used to regulate bleeding and may also help with symptoms related to higher androgen activity, including acne and excess hair growth.
Metformin may be recommended for some people, particularly where metabolic features are a concern. It improves the body's response to insulin and can have additional benefits depending on an individual's situation.
If you're trying to become pregnant and aren't ovulating regularly, fertility treatment is available too. Current international guidelines recommend letrozole as the first-line medication for ovulation induction in many people with PMOS-related anovulatory infertility where there are no other infertility factors. Other medications and assisted reproductive treatments such as IVF may be considered when appropriate. (PubMed Central (PMC))
Healthy eating and regular physical activity are also recommended for everyone with PMOS for their general health and metabolic benefits. (World Health Organization)
Healthcare around PMOS has historically focused heavily on weight but current guidance places more emphasis on individual health, sustainable behaviours and avoiding weight stigma.
What about supplements for PMOS?
This is one area where social media can make things look much more clear-cut than the science actually is and we always recommend you get advise from a medical professional before going crazy and buying up any kind of suppliment.
You'll see plenty of supplements marketed specifically for PCOS or PMOS, particularly inositol, vitamin D and magnesium.
Inositol has attracted significant research interest, and current international guidance says it may be considered based on individual preferences, with the potential for some improvements in metabolic measures. However, evidence for meaningful clinical benefits is still limited, and guidelines currently cannot recommend one particular type, dose or combination of inositol based on the available evidence. (PubMed Central (PMC))
Vitamin D or other supplements may be appropriate if testing identifies a deficiency, but that is VERY different from saying everyone with PMOS should routinely take them.
So, as we said, it's worth talking to your doctor, pharmacist or dietitian before spending a fortune on a shelf full of supplements - particularly if you're taking medication or trying to conceive.
Managing heavy or unpredictable periods
Even when you're working on the medical side of PMOS, there's still the practical question of dealing with the period that turns up when it feels like it.
Having period care you trust can make unpredictable bleeding considerably less stressful.
For people comfortable using internal period products, the Hello Disc can be particularly useful for heavier days because it has a much higher capacity than a standard tampon and can be worn for up to 12 hours depending on your flow.
The Hello Cup is another reusable internal option, while Hello Period's Reusable Pads and Hello Period Undies can provide external protection on their own or as backup when your cycle is being especially unpredictable.
Some people with irregular cycles also like keeping period undies, reusable pads or another product in their bag simply because they don't always have much warning before bleeding begins.
Whatever products you use, remember that suddenly developing extremely heavy bleeding isn't something you should automatically write off as "just PMOS". If you're soaking through period products very quickly, feeling faint or dizzy, passing unusually large clots, experiencing severe pain or concerned about the amount you're bleeding, seek medical advice.
Living with PMOS
One of the frustrating things about PMOS is how differently it can affect different people.
You may have a friend with the condition whose experience looks nothing like yours. Their periods might disappear while yours become heavy. Their main concern might be acne while yours is fertility, hair growth, fatigue or metabolic health.
A good healthcare plan should take your individual symptoms, priorities and stage of life into account rather than trying to squeeze everyone into the same treatment plan.
And if you've spent years knowing the condition as PCOS, you don't need to panic about suddenly using the "wrong" term either. PCOS hasn't become a different disease. PMOS is a better name for the condition we already knew about.
The aim of the change is to move the conversation away from misleading "ovarian cysts" and towards a more accurate understanding of a complex condition involving hormones, metabolism, ovarian function and health across a lifetime.
For now, PCOS and PMOS will exist side by side while healthcare catches up.
Hopefully, the end result isn't simply a new acronym to remember. It's better recognition, earlier diagnosis and better care for the millions of people living with it.
This article provides general information only and isn't a substitute for individual medical advice. If you're concerned about irregular periods or other possible PMOS/PCOS symptoms, talk to your GP or another qualified healthcare professional.
References
-
World Health Organization. Polycystic ovary syndrome. Updated 22 January 2026.
-
Teede HJ, Bahri Khomami M, Morman R, et al. Polyendocrine metabolic ovarian syndrome, the new name for polycystic ovary syndrome: a multistep global consensus process. The Lancet. 2026;407:2329–2339.
-
Monash Centre for Health Research and Implementation. PCOS Guideline / PMOS Guideline. 2026.
-
Teede HJ, Tay CT, Laven J, et al. Recommendations from the 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome. Journal of Clinical Endocrinology & Metabolism. 2023;108(10):2447–2469.
-
Endocrine Society. Polyendocrine Metabolic Ovarian Syndrome: New name to improve diagnosis and care of condition affecting 170 million women worldwide. 12 May 2026.
-
American Society for Reproductive Medicine. PCOS is Now PMOS: Understanding the Name Change. 27 May 2026.
-
Kordowitzki P, Teede H. Polyendocrine metabolic ovarian syndrome — a new name for an old problem. Nature Metabolism. 2026;8:1443–1445.